Pigmented nevus
Melanocytic nevi (also known as nevi or moles) are formed by Focal proliferation of melanocytes a benign skin growth.
Real mole-removal cases by our physician
The following four cases were personally evaluated and treated by our physician at our Nanjing clinic, with Media Release Form authorization on file. Pigmented nevi vary significantly by type; some lesions must first rule out malignancy. Actual protocols are determined at consultation based on ABCDE evaluation.
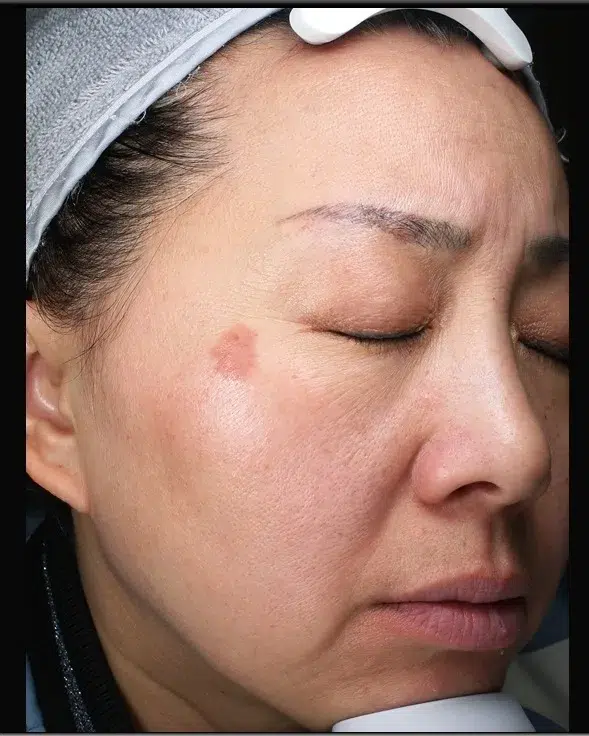
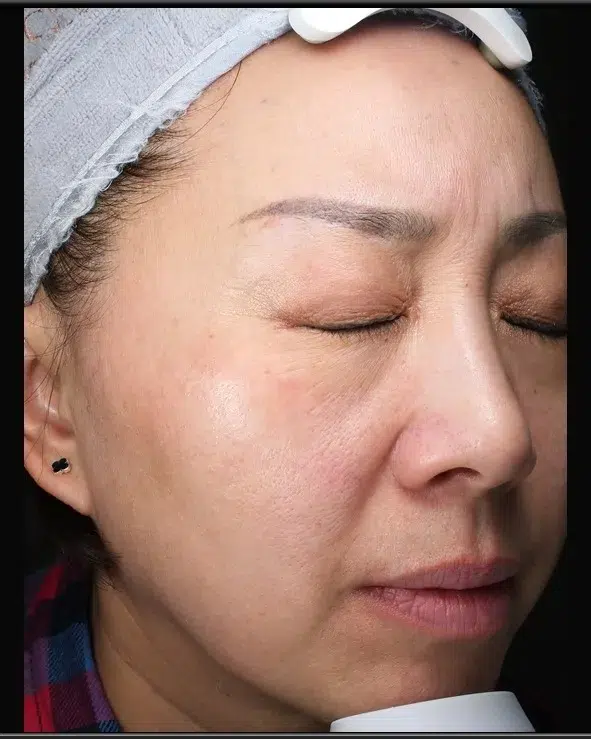
Case 4 · Real Pigmented Nevus Record
- Client profile
- Asian female · Fitzpatrick IV
- Concerns addressed
- Melanocytic nevi (comprehensive improvement with a multi-modal combination protocol)
- Treatment plan
- Dual Picosecond Combination Therapy + PicoSure® + PicoSure Pro® + PicoWay® (multiple sessions within 3 months)
- Improvement
- Marked improvement of pigmented nevus · natural overall result
- PIH
- No PIH
- Maintenance
- Daily sun protection + monthly home care + quarterly assessments
Case 04: Pigmented nevus before treatment · Asian female · Fitzpatrick IV · Multimodal combination protocol led by our physician at Luowei Medical Aesthetics Clinic, Nanjing.
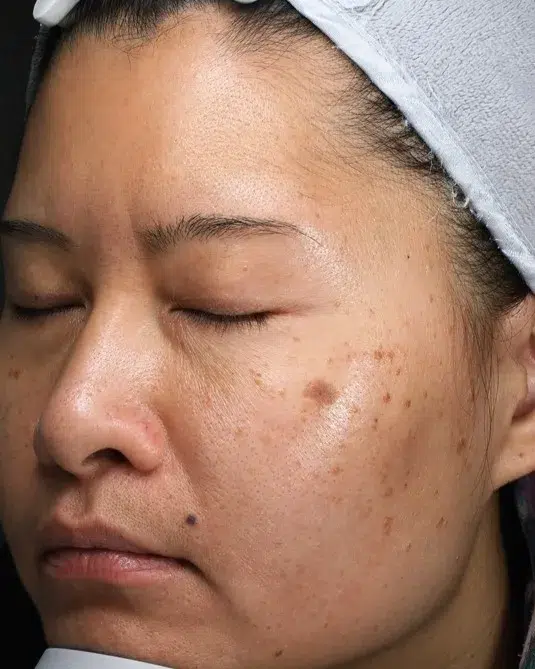
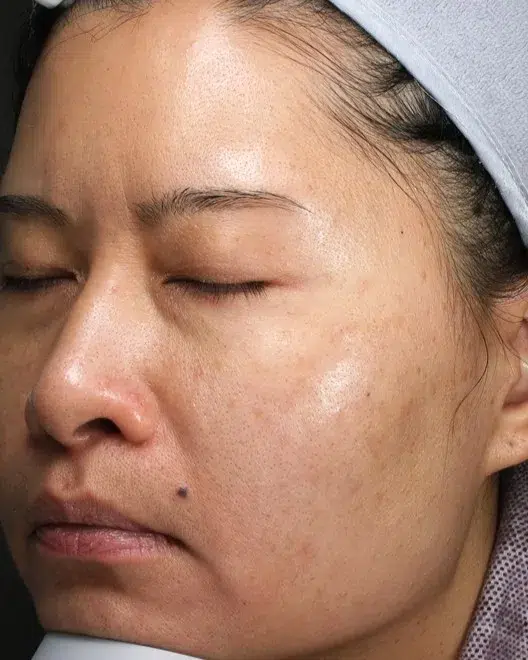
Case 42 · Real Pigmented Nevus Record
- Client profile
- Asian female · Fitzpatrick IV
- Concerns addressed
- Melanocytic nevi (comprehensive improvement with a multi-modal combination protocol)
- Treatment plan
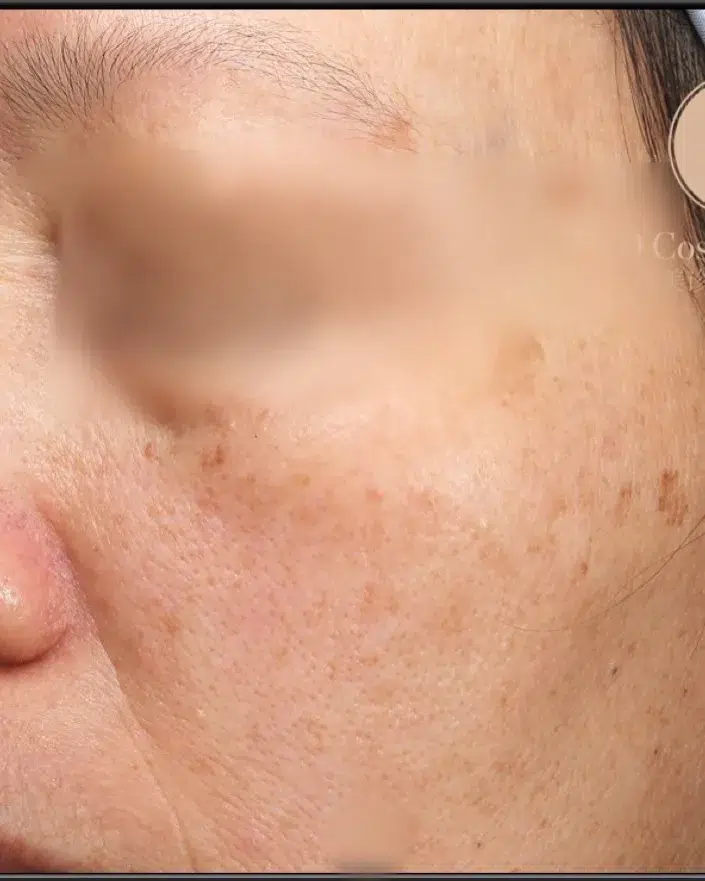
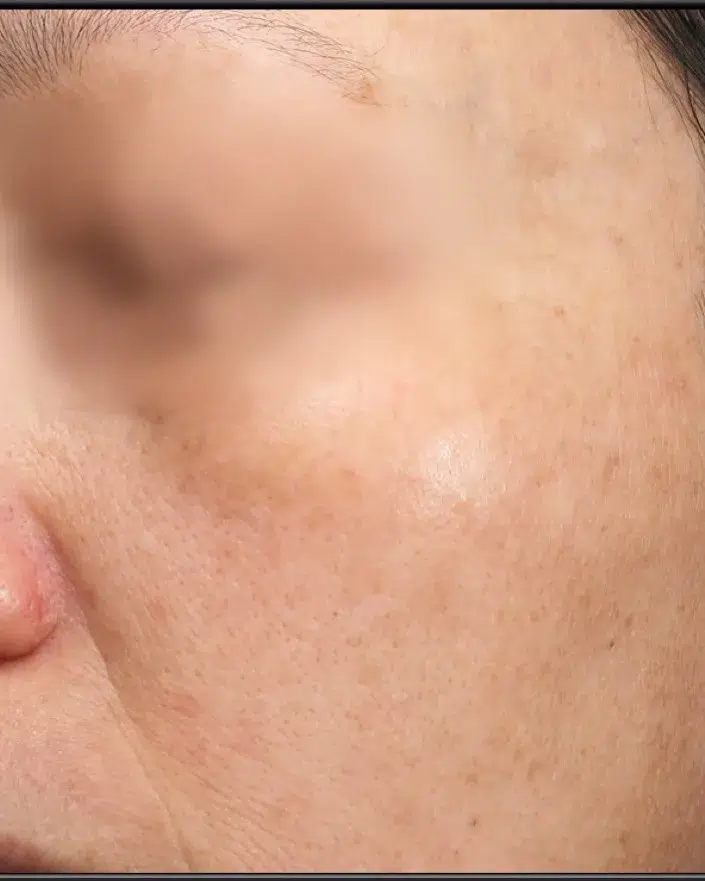
- PicoSure® + PicoSure Pro® + PicoWay® (multiple sessions within 3 months)
- Improvement
- Marked improvement of pigmented nevus · natural overall result
- PIH
- No PIH
- Maintenance
- Daily sun protection + monthly home care + quarterly assessments
Case 42: Melanocytic nevi before & after · Asian female · Fitzpatrick IV · Multi-modal combination protocol led by our physician at Luowei Medical Aesthetics Clinic, Nanjing
Case 45 · Real pigmented nevus record
- Client profile
- Asian female · Fitzpatrick IV
- Concerns addressed
- Melanocytic nevi (comprehensive improvement with a multi-modal combination protocol)
- Treatment plan
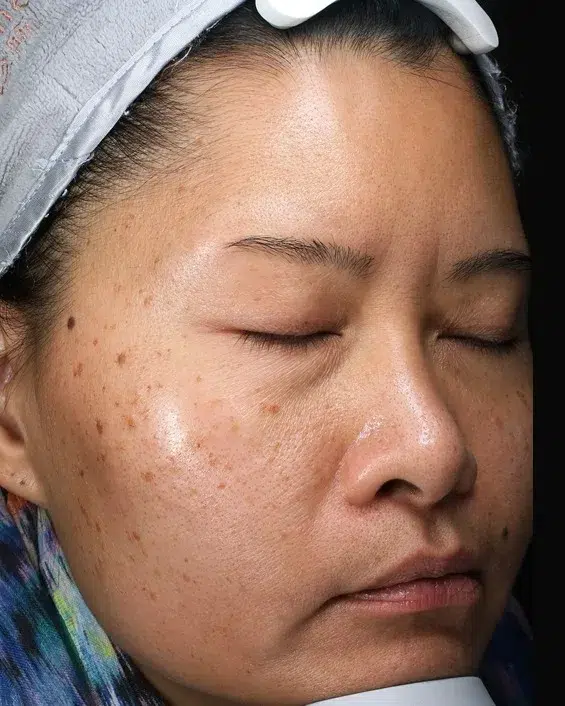
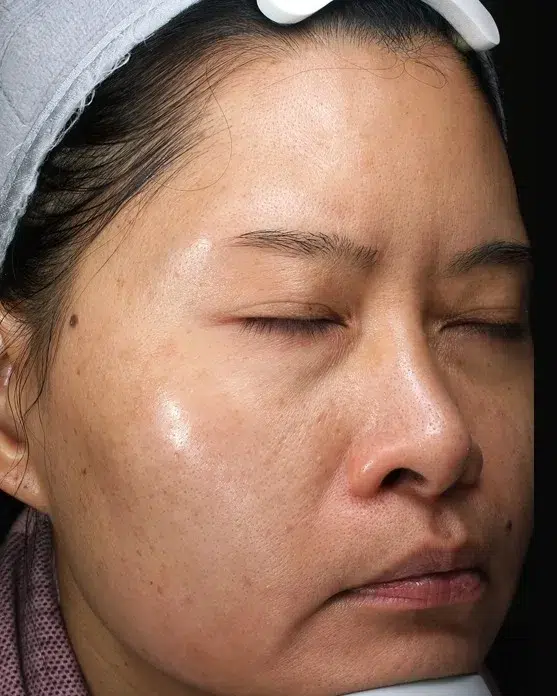
- Dual Picosecond Combination Therapy + PicoSure® + PicoSure Pro® + PicoWay® (multiple sessions within 3 months)
- Improvement
- Marked improvement of pigmented nevus · natural overall result
- PIH
- No PIH
- Maintenance
- Daily sun protection + monthly home care + quarterly assessments
Case 45: Pigmented Nevus Before Comparison · Asian Female · Fitzpatrick IV · Multi-Modal Combination Protocol Led by our physician at Luowei Medical Aesthetics Clinic Nanjing
Case 49 · Real mole-removal record
- Client profile
- Asian female · Fitzpatrick IV
- Concerns addressed
- Melanocytic nevi (comprehensive improvement with a multi-modal combination protocol)
- Treatment plan
- Dual Picosecond Combination Therapy + PicoSure® + PicoSure Pro® + PicoWay® (multiple sessions within 3 months)
- Improvement
- Marked improvement of pigmented nevus · natural overall result
- PIH
- No PIH
- Maintenance
- Daily sun protection + monthly home care + quarterly assessments
Case 49: Pigmented nevus before treatment · Asian female · Fitzpatrick IV · Multimodal combination protocol led by our physician at Luowei Medical Aesthetics Clinic, Nanjing.
What is a melanocytic nevus? Why is it different from ordinary pigmented spots or skin tags?
Melanocytic nevi (also known as nevi or moles) are formed by Focal proliferation of melanocytes a benign skin growth. It is not pigmentation, and it is not a skin tag — it is a distinct A true cellular lesion. The vast majority are benign and remain stable for life; only a very small minority undergo atypical change or even progression to melanoma. The first step in pigmented nevus treatment has never been laser, but Benign vs. malignant assessment.
Why It Cannot Be Treated as Pigmentation
Pigmented spots are melanin “deposits” — a laser only needs to shatter the pigment particles. Melanocytic nevi are Melanocyte “solid” lesion, Must be removed by vaporizing or excising the entire cell cluster; otherwise residual cells will inevitably recur.
Why can’t moles be treated like skin tags?
Skin Tag These are epidermis plus fibrous tissue, contain no melanocytes, and can be simply snipped off. If a pigmented nevus is misclassified as a skin tag and treated with electrocautery snipping, residual roots will lead to recurrence, and the opportunity for pathological evaluation will be lost.
Why is ABCDE assessment mandatory first?
ABCDE(Asymmetry / Border / Color / Diameter / Evolution)is the internationally recognized screening standard for benign versus malignant pigmented nevi. Any positive finding should not be lasered directly — referral to dermatopathology is required first.
Why do we take dermoscopy images before treatment?
Dermoscopy magnifies 10–20× to assess whether the pigment network is regular and whether vascular abnormalities exist — clinical evidence that cannot be obtained by the naked eye, and the core of our physician’s principle: “no typing, no laser.”
Clinical highlights:In our Nanjing practice, we’ve seen too many clients walk into a medspa for quick “mole zapping” and end up with (1) scarring, (2) residual recurrence, or — most seriously — (3) early melanoma ablated as a routine mole, missing the diagnostic window. Our physician’s mole protocol The first step is always benign-versus-malignant evaluation, rather than simply firing up the laser.
Causes and Five Clinical Types of Pigmented Nevi
The formation of pigmented nevi is Genetics + UV exposure + melanocyte migration the result of multiple overlapping factors. Based on the distribution of melanocytes within the skin layers, pigmented nevi are clinically classified into the following 5 main types.
1. Junctional Nevus
Melanocytes located at Junction between epidermis and dermis, Clinically presents as Flat brown nevus. Common in children and young adults; usually stable. Responds best to laser treatment.
2. Compound Nevus
Melanocytes are present in both Dermo-epidermal junction + superficial dermis, Clinically presents as Slightly raised dark brown moles. Requires layered treatment of both epidermal and dermal components.
3. Intradermal Nevus
Melanocytes are located entirely in Dermis, Clinically presents as Dome-shaped, flesh-coloured or light-brown raised lesion. Common in middle-aged and older adults; laser treatment focuses primarily on “volume removal”.
4. Blue Nevus
Deep-dermis melanocytes, clinically presenting as Blue-gray firm nodule. requires careful evaluation; some blue nevi carry malignant potential, so dermatopathology assessment is the first choice.
5. Atypical / Dysplastic Nevus
shares certain melanoma features (asymmetry, irregular borders, multiple colours),Considered a potentially high-risk lesion. In principle No cosmetic laser, Referral to dermatology for surgical excision and pathology.
⚠️ Key principle:Classification determines not only the treatment method but also“can it be treated”. Our physician insists on Any mole with ABCDE warning signs is referred — never treated cosmetically— This is the standard upheld by a physician, not a medspa technician.
4 skin lesions commonly mistaken for pigmented nevi — key differential diagnosis points
“they all look like dark spots — but they are fundamentally different and require entirely different management. Misclassification may at best cause scarring and recurrence, and at worst delay melanoma diagnosis.
Skin Tag
Acrochordon · Soft fibroma
| Tissue | Epidermis + fibrous tissue,No melanocytes |
|---|---|
| Morphology | Soft pedunculated small papules, flesh-colored or light brown |
| Commonly occurs | Neck, underarms, and around the eyes |
| Risk of malignant transformation | None |
| First-line treatment | Electrocautery / micro-excision, simple |
Seborrheic keratosis (age spots / SK)
Seborrheic Keratosis
| Tissue | Epidermal hyperkeratosis,Contains pigment but no nevus cells |
|---|---|
| Morphology | “waxy brown-black patches that look” stuck on “ |
| Commonly occurs | 40 and older, on the face or trunk |
| Risk of malignant transformation | Extremely low |
| First-line treatment | eCO2 / Q-switched laser, with good results |
Solar lentigo (sun spots / age spots)
Solar Lentigo · Age Spot
| Tissue | increased melanin in the basal epidermis,No nevus cell nests |
|---|---|
| Morphology | Flat, well-demarcated brown macules |
| Commonly occurs | Areas of cumulative sun exposure |
| Risk of malignant transformation | Extremely low |
| First-line treatment | PicoSure Pro Single-session removal |
Melanoma
Malignant Melanoma · Warning lesions
| Tissue | Melanocytes Malignant proliferation, Can invade the dermis and blood vessels |
|---|---|
| Morphology | Asymmetry / irregular borders / multiple colours / diameter >6mm / Changes |
| Commonly occurs | Can occur anywhere; relatively higher incidence on the sole and subungual area in Asians |
| Risk of malignant transformation | Already malignant · Curable when caught early |
| First-line treatment | Immediate referral to Dermatology + pathology biopsy · No laser |
⚠️ Warning:Every year we see clients in clinic who come in with“already lasered elsewhere and recently regrew” lesions come to us — these are not “recurrences,” but Early lesions that should have been referred were instead mistakenly vaporized by laser, while deeper cells continued to grow. A seemingly convenient “mole zap” can delay diagnosis by 1–2 years — and the cost is irreversible.
ABCDE Five-point self-check — which moles need immediate medical evaluation?
Internationally recognized dermatologic screening standard for benign vs. malignant nevi.Any one match warrants immediate consultation, Do not attempt laser first.
Asymmetry
Asymmetry
If the mole is cut in half and the two sides differ in shape → warning sign. Benign nevi are usually symmetrical.
Border
Irregular borders
Jagged, blurred, or notched borders → warning sign. Benign moles have smooth, well-defined borders.
Color
Varied colors
Multiple colours within a single mole (black, brown, red, blue, white) → warning sign. Benign moles are uniform in colour.
Diameter
Excessive diameter
Diameter >6mm((roughly the size of a pencil eraser) → warning sign. However, small moles can also undergo malignant change, so size alone cannot rule it out.
Evolution
Recent changes
recent change in size / color / shape / height, or new itching, bleeding or ulceration → The most important warning sign.
⚠️ Self-examination cannot replace physician assessment:ABCDE is a public education tool, not a diagnostic standard. Early-stage melanoma can fully present with a “benign appearance.” During consultation, our physician combines it with Dermoscopic magnified examination, Can identify pigment network abnormalities invisible to the naked eye.
5 Treatment Options for Pigmented Nevi — Selected by Classification
There is no “miracle mole remover.” Every mole must be assessed based on Subtype + depth + location + benign/malignant assessment to select the most appropriate tool.
ECO2 Fractional CO₂ Laser
10600nm Far-infrared wavelength absorbed by water → precise tissue ablation.Gold standard for compound and intradermal nevi, allows layered depth control and single-pass clearance of dermal nevus cell clusters. Our physician’s protocol emphasizes“Better two shallow sessions than one that goes too deep”, significantly reducing the risk of scarring.
Q-switched 1064 nm / 532 nm
Nanosecond pigment-selective laser, suitable for Flat junctional nevi. 532nm treats superficial brown pigment; 1064nm treats deeper pigment. Fitzpatrick III–V Asian skin requires Low-energy staged sessions Avoiding PIH rebound.
Picosecond Lasers (PicoSure Pro / PicoWay)
Picosecond ultra-short pulse width + photomechanical effect, suitable for Superficial flat moles + simultaneous improvement of surrounding skin. Minimal thermal damage; lowest PIH risk for Asian skin.
Surgical excision + sutures + pathology
All ABCDE-positive findings, atypical nevi, blue nevi, and diameter >6mm of the lesion The only correct choice. Our physician does not perform these procedures in clinic and will refer directly to public-system Dermatology or Plastic Surgery.
Post-procedure recovery protocol
Includes topical antibiotic ointment + tension-relief tape + strict mineral SPF 50+ (with iron oxide) + silicone sheets when needed for scar prevention. For Asian skin, post-procedure 4–12 Weeks of sun protection determine the final result.
Our physician’s 6-Step Standard Protocol for Pigmented Nevi
Consultation + ABCDE evaluation + dermoscopy
30 -minute free consultation — Our physician personally performs the 5-point ABCDE assessment + magnified dermoscopy on every lesion to be treated.No assessment, no laser.
Classification-based decision (treat / refer)
Clearly identify whether each mole is Cosmetically treatable ((benign junctional / compound / intradermal) or Referral required (ABCDE positive findings / atypical / blue nevus / sensitive location). Our physician would rather decline a case than risk misjudging one.
Device selection + depth planning
Flat moles → Q-switched / picosecond; raised moles → layered eCO₂; mixed → combination protocol.More conservative parameters are always used in high-exposure facial zones Avoid scarring.
Main treatment phase (1–2 sessions)
Topical anesthetic for 30 minutes + precise technique + immediate cold compress. Energy is assessed individually for each lesion — no batch treatment. Antibiotic ointment and a recovery plan are prescribed right after the procedure.
Recovery phase (7–14 days for scabs to fall off naturally)
During the scabbing phase, never peel or pick. The newly formed epidermis under the scab is pink and matures over 4–8 weeks.Strict physical sun protection throughout the entire recovery period Avoid PIH.
Assessment phase (8–12 weeks post-procedure) + annual follow-up
Assess for the need of touch-ups, residual pigment, or recurrence. Annual follow-up is recommended with full-body dermoscopy, especially for patients with a family history of melanoma or multiple atypical nevi.
Pigmented Nevus Treatment Timeline — How Long Until Full Recovery?
| Typing / device selection | Number of sessions | Scabbing phase | Pink-mark phase | Fully fades |
|---|---|---|---|---|
| Flat junctional nevus / Q-switched | 1–2 sessions | 5–7 days | 4–8 weeks | 2–3 months |
| Compound nevus / eCO2 | 1–2 sessions | 7–10 days | 4–12 weeks | 3–6 months |
| Intradermal nevus / eCO2 (deep) | 1 sessions | 10–14 days | 8–12 weeks | 4–6 months |
| Large lesions / multiple-mole combinations | 2–3 sessions | Staged scabbing | Staged healing | 6–9 months |
Clinical note:Pigmented nevus treatment may appear to be “a single session,” but in reality Final skin-tone matching takes 3–6 months. Pink marks and very mild PIH during this period are normal. For Asian skin, sun protection sets the ceiling of your result — without SPF 50+ physical sunscreen, outcomes are compromised.
Is your pigmented nevus suitable for laser treatment? 2-minute self-assessment
✅ Suitable to begin assessment
- ✓Mole is symmetrical in shape, uniform in colour, with well-defined borders
- ✓Stable for years, with no recent changes
- ✓Diameter <6mm((smaller than a pencil eraser)
- ✓Primarily for cosmetic, psychological, or repeated-friction reasons
- ✓Willing to accept the concept of a recovery period plus long-term follow-up
- ✓ABCDE assessment + dermoscopy before any treatment
❌ Requires pathology evaluation first; direct laser is not recommended
- ✗Change in size / color / shape over the past 6–12 months
- ✗Itching, bleeding, ulceration or satellite lesions appear
- ✗Irregular borders with multiple colors (black + red + blue + white)
- ✗Diameter >6mm and newly appearing or growing
- ✗Blue nevus / large congenital nevus / atypical nevus
- ✗First-degree relative with a history of melanoma
Luowei Medical Mole Removal vs. Standard MedSpa Mole Removal
- ✗A quick glance and zap, with no ABCDE assessment
- ✗No magnified dermoscopy examination
- ✗Treating junctional / compound / intradermal nevi with a single device, without differentiation
- ✗Procedures are mostly performed by aestheticians / RMTs, with no physician consultation
- ✗Cannot recognize melanoma warning signs — potentially malignant lesions get lasered anyway
- ✗Too deep in one pass → scarring; too superficial → recurrence
- ✗No post-procedure recovery follow-up; patients are left to manage scarring or PIH on their own
- ✓ABCDE 5-criteria assessment is mandatory
- ✓Dermoscopy (magnified examination)
- ✓eCO₂ / Q-switched / picosecond / referral, selected by subtype
- ✓Personally assessed and treated by our physician
- ✓Any ABCDE-positive finding is proactively referred to dermatology — never forced into treatment
- ✓Layered depth control — better to stage shallow passes than go too deep at once
- ✓Complete 6-step protocol including post-procedure recovery and annual follow-up
Why can you trust Luowei Medical Aesthetics Clinic’s pigmented nevus content?
Experience
Expertise Specialty
Dermoscopy training · Cynosure / Lutronic advanced certification · Multi-device protocols
Authoritativeness Authoritative
Pathology referral credentials · Published author
Trustworthiness Trustworthy
All cases on this page are used with Media Release authorization · ABCDE-positive cases are proactively referred
About pigmented nevus treatment pricing
Mole removal pricing varies widely between clinics — but the core of the cost has never been the laser device itself; it lies in Who evaluates whether each mole is suitable for laser, and who judges the risk of malignancy, and how deeply clinical experience must be involved. Pigmented nevi are unlike ordinary pigmentation — they involve lesion classification, benign/malignant assessment, and when needed, referral to dermatopathology. These judgments can only be made by a licensed physician. At Luowei Medical Aesthetics Clinic, our physician is personally and deeply involved in the evaluation and treatment of pigmented nevi, and the pricing structure reflects this investment of medical resources and clinical judgment. For select cases that our physician has clearly evaluated as benign and that require only simple edge-refinement maintenance, our trained medical team may safely perform the procedure under our physician’s protocol, making care more accessible. The price gap in laser treatment fundamentally comes from physician operation and techniqueClinical experience differs significantly between physician and technician operation. For any step involving benign-versus-malignant assessment, we insist the physician personally performs it. Which protocol suits you is determined by the nature of the lesion itself, not by price — the specific plan will be discussed at your consultation based on ABCDE evaluation and dermoscopy.
- Payment is made at the clinic, after the consultation and before treatment begins
- Nothing is paid in advance, and no deposit is required to hold an appointment
- Cosmetic treatment is a self-pay item and is not covered by public medical insurance in China
- All first-time patients receive a 30-minute Complimentary Consultation & assessment
Risks & Contraindications — what we have to tell you upfront
What are the main risks of laser mole removal?
1. Scarring / depression((treating too deeply or too aggressively): mitigated through layered depth control and staged sessions; 2. Residual pigment / recurrence(treated too superficially): can be re-treated after an 8–12 week reassessment; 3. PIH(moderate risk on Asian skin): significantly reduced by strict sun protection + a low-energy protocol; 4. Infection((rare, due to improper aftercare): prevented with antibiotic ointment; 5. Misdiagnosis of a malignant lesion: Avoided through ABCDE + dermoscopy assessment and, when indicated, referral for pathology — This is the most critical risk in pigmented nevus treatment.
Which Moles Should Absolutely Not Be Lasered?
ABCDE Any positive ABCDE finding, atypical / dysplastic nevus, blue nevus, large congenital nevus, recently changing mole, bleeding / ulcerated / itchy mole, first-degree relative with a history of melanoma, or moles on the sole, subungual area, or mucosa — in these cases our physician will not perform cosmetic laser treatment, and will recommend referral to dermatology with pathology biopsy.
How do I care for the area post-treatment to avoid scarring and PIH?
Six core steps: (1) During the scabbing phase (5–14 days), never pick or peel; let scabs fall off naturally; (2) Apply topical antibiotic ointment daily to prevent infection; (3) Begin strict mineral SPF 50+ (with iron oxide) immediately after scabs fall off; (4) Avoid sun exposure, saunas, and prolonged heat for 3 months; (5) Patients prone to scarring may consider silicone sheets for prevention; (6) Return immediately if you notice redness, swelling, heat, pain, or abnormal discharge.
What Does the Informed Consent Form Include?
Every client signs an Informed Consent before their first treatment, covering: treatment mechanism, possible adverse reactions and their probability, risk of scarring/recurrence, ABCDE assessment conclusion, alternative options (including pathology referral), post-procedure care, follow-up schedule, and Media Release (voluntary). Every item is explained by our physician in person — not signed off by a receptionist.
Where the medical claims on this page come from
Everything above about Pigmented nevus rests on published evidence rather than on our own word. The sources below are the ones behind those statements: peer-reviewed papers indexed in PubMed, and guidance written for patients by dermatology academies and national health services. Read them before you decide — and bring any of them to your consultation.
- Peer-reviewedGuidelines of care for the management of acne vulgaris
- Peer-reviewedPostinflammatory hyperpigmentation: A comprehensive overview: Epidemiology, pathogenesis, clinical presentation, and noninvasive assessment technique
- Peer-reviewedMelasma Treatment: An Evidence-Based Review
- Peer-reviewedChemical peels for darker skin types
- Patient guidanceAcne: Tips for managing
- Patient guidanceMelasma: Treatment
What these references can and cannot tell you. They describe what is known about the treatment itself — how well it tends to work, how long results last, and what can go wrong. They are not an assessment of this clinic, and no published study can tell you whether it suits your skin type, anatomy, or medical history. That judgement comes from the physician who examines you in person, and it may well be “not this one”.