Post-Inflammatory Hyperpigmentation (PIH)
What is post-inflammatory hyperpigmentation (PIH)? How is it different from acne scarring and melasma?
Real Patient Cases: Our physician’s PIH Treatment Results
The following four cases were personally treated by our physician at our Nanjing clinic and are shared with written Media Release authorization. PIH from acne has varied causes and distinct subtypes; individual responses differ. Actual outcomes are determined through a face-to-face consultation and assessment.
Case 1 · Documented PIH Treatment Journey
- Client profile
- Asian Female · Fitzpatrick I · Duration: 6–12 Months
- Primary concern
- VISIA Assessment · Post-Inflammatory Hyperpigmentation (PIH) · Post-Acne Sequelae
- Treatment plan
- PicoSure® + Vbeam® sensitive skin repair (3–4 sessions)
- Improvement
- Significant improvement in post-inflammatory hyperpigmentation · Natural-looking overall result
- Risk of rebound hyperpigmentation
- No PIH
- Maintenance
- Mesotherapy Monthly × 3 sessions + at-home retinoid + SPF 50+
Case 01: Post-Inflammatory Hyperpigmentation — Before & After · Asian Female · Fitzpatrick I · Duration: 6–12 months · Multimodal combination protocol led by our physician at Luowei Medical Aesthetics Clinic, Nanjing


Case 2 · Post-Inflammatory Hyperpigmentation — Real Patient Record
- Client profile
- Asian Female · Fitzpatrick IV · Duration: approximately 3–5 years
- Primary concern
- Post-Inflammatory Hyperpigmentation (Comprehensive Improvement with Multimodal Combination Therapy)
- Treatment plan
- Fotona® redness-reduction laser + laser vascular clearance + Vbeam® intense pulsed dye laser + Vbeam® diffuse redness treatment — and 12 additional modalities (single session)
- Improvement
- Significant improvement in post-inflammatory hyperpigmentation · Natural-looking overall result
- Risk of rebound hyperpigmentation
- No PIH
- Maintenance
- Sofwave/Ultherapy 18-24 months of maintenance with home skincare
Case 02: Post-Inflammatory Hyperpigmentation (PIH) — Before & After · Asian Female · Fitzpatrick IV · Duration: ~3–5 Years · Multimodal combination protocol led by our physician at Luowei Medical Aesthetics Clinic, Nanjing
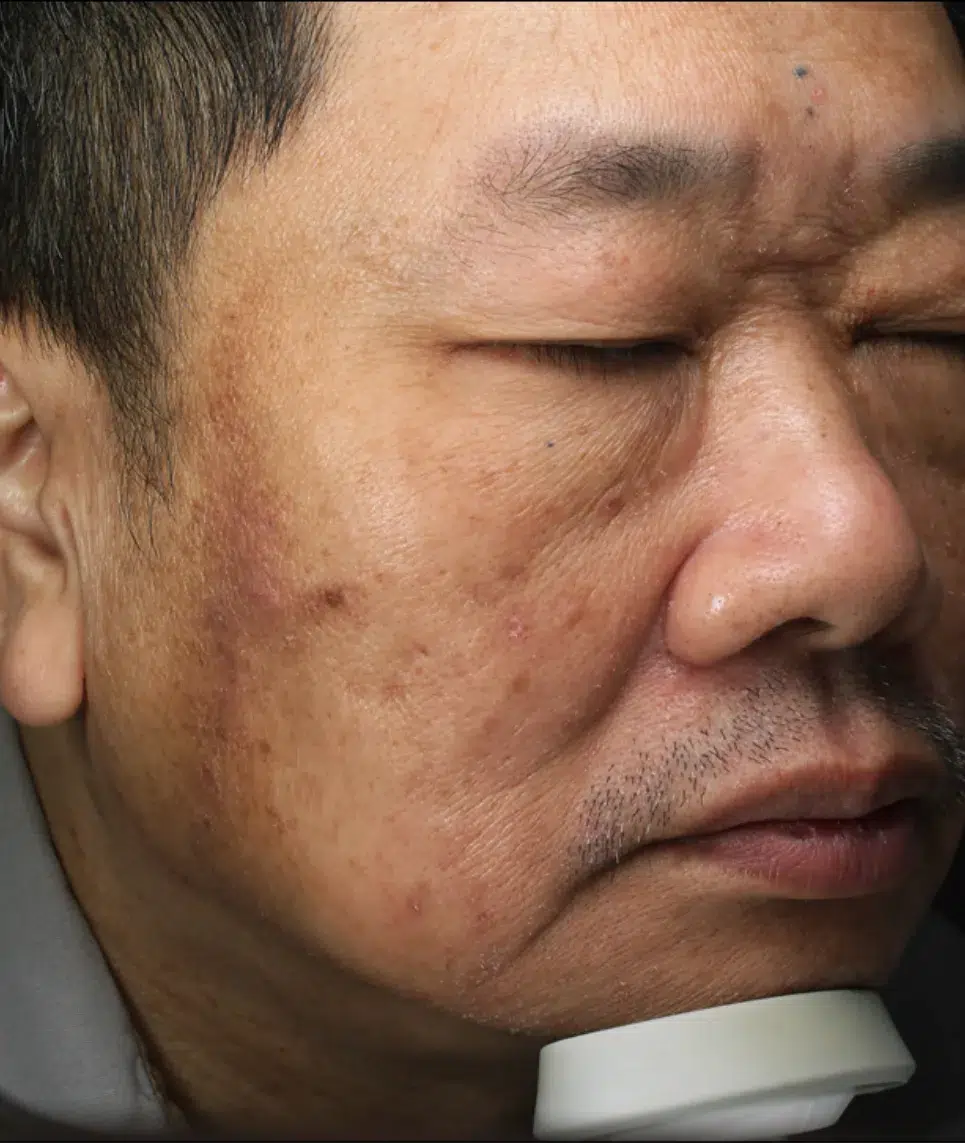
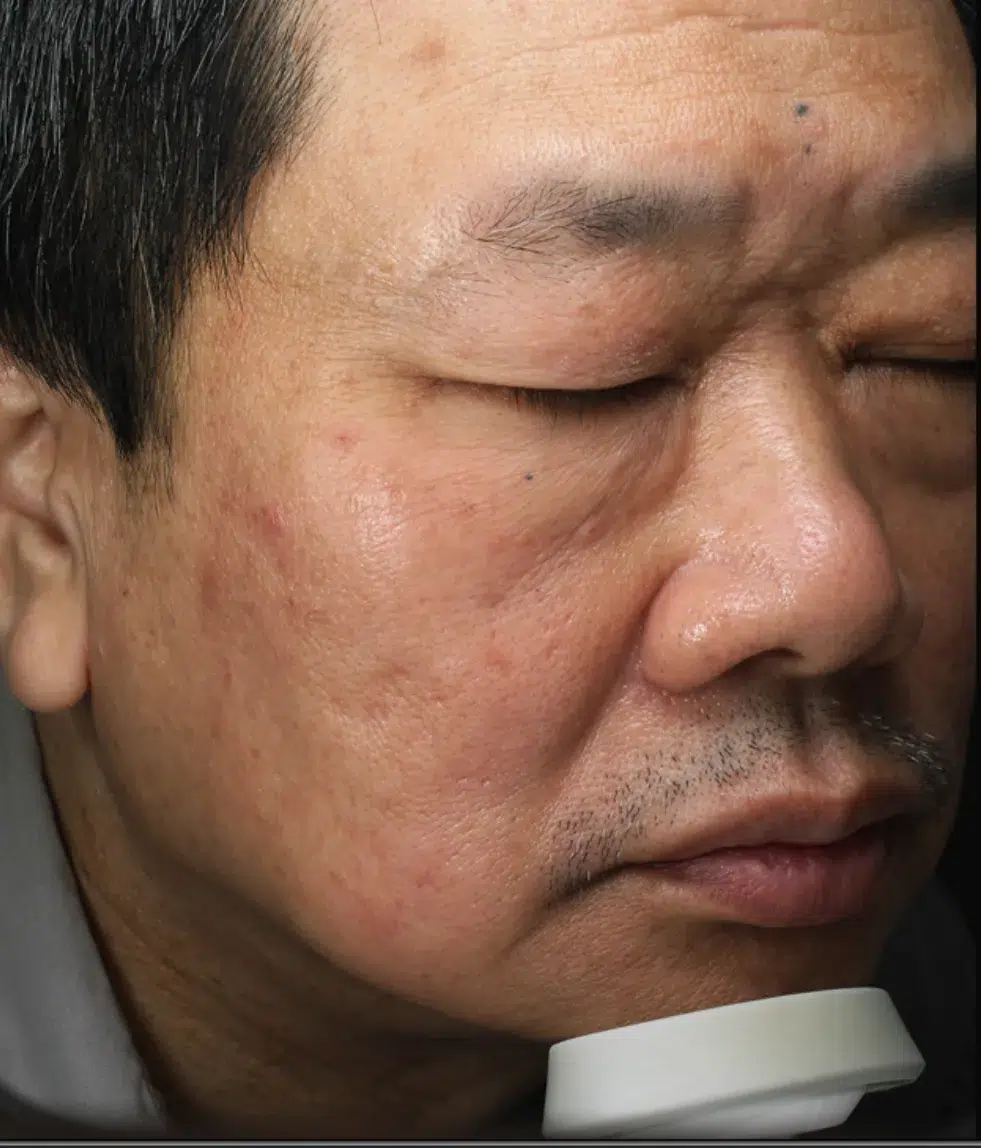
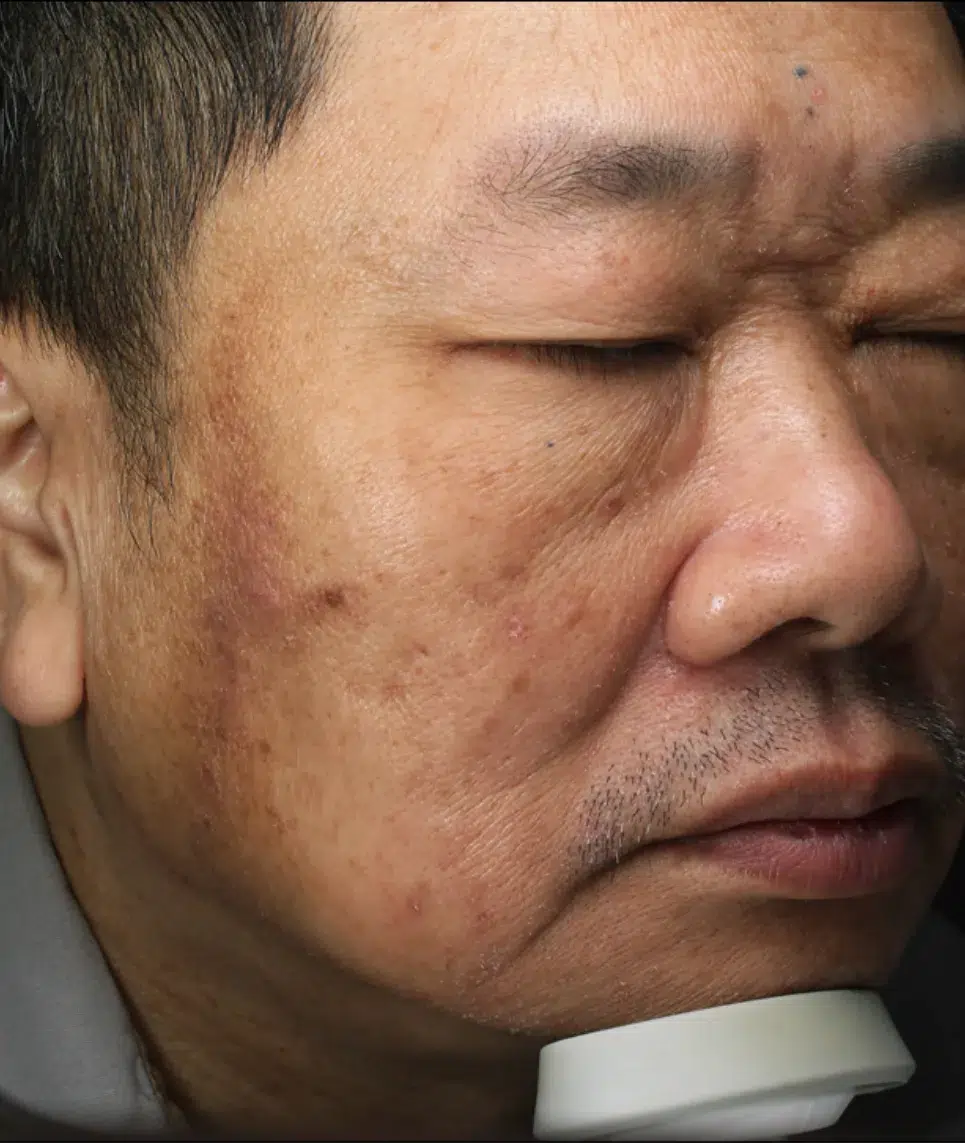
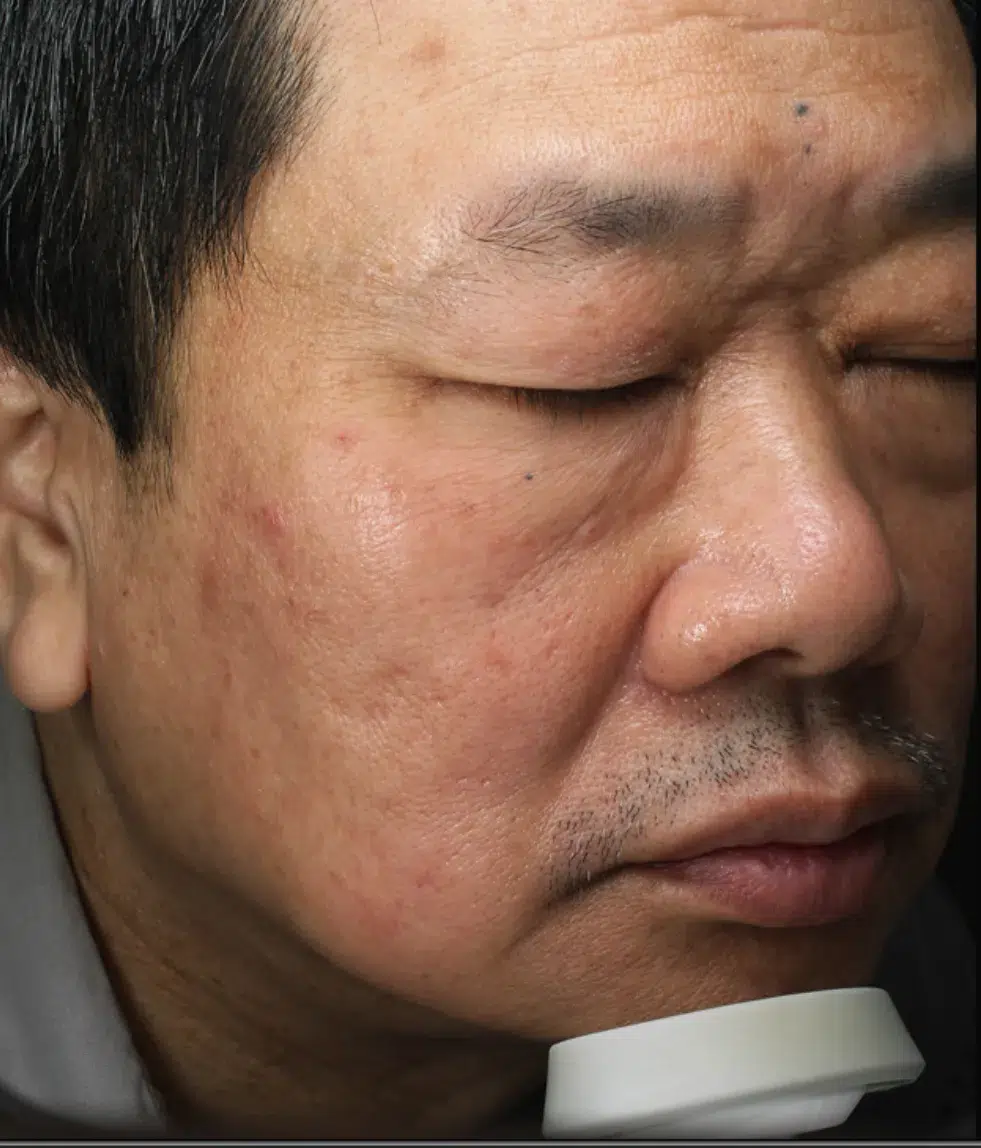
Case 3 · Post-Inflammatory Hyperpigmentation — Documented Results
- Client profile
- Asian Male · Fitzpatrick IV
- Primary concern
- Post-Inflammatory Hyperpigmentation (Comprehensive Improvement with Multimodal Combination Therapy)
- Treatment plan
- Dual picosecond combination therapy + Pico® brightening & skin rejuvenation + PicoSure® + PicoSure Pro® and 5 other modalities (multiple sessions within 3 months)
- Improvement
- Significant improvement in post-inflammatory hyperpigmentation · Natural-looking overall result
- Risk of rebound hyperpigmentation
- No PIH
- Maintenance
- Annual review + long-term SPF 50 · Booster sessions as needed
Case 03: Post-Inflammatory Hyperpigmentation — Before & After · Asian Male · Fitzpatrick IV · Multimodal combination protocol led by our physician, at Luowei Medical Aesthetics Clinic, Nanjing
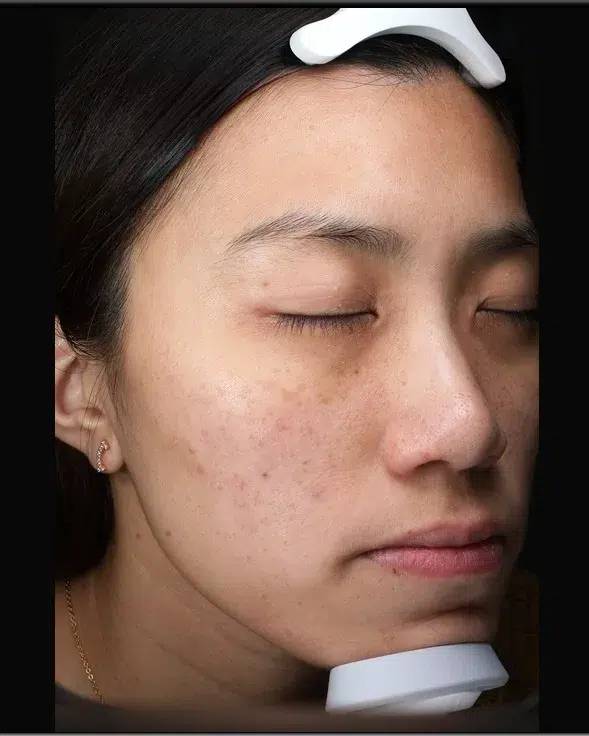
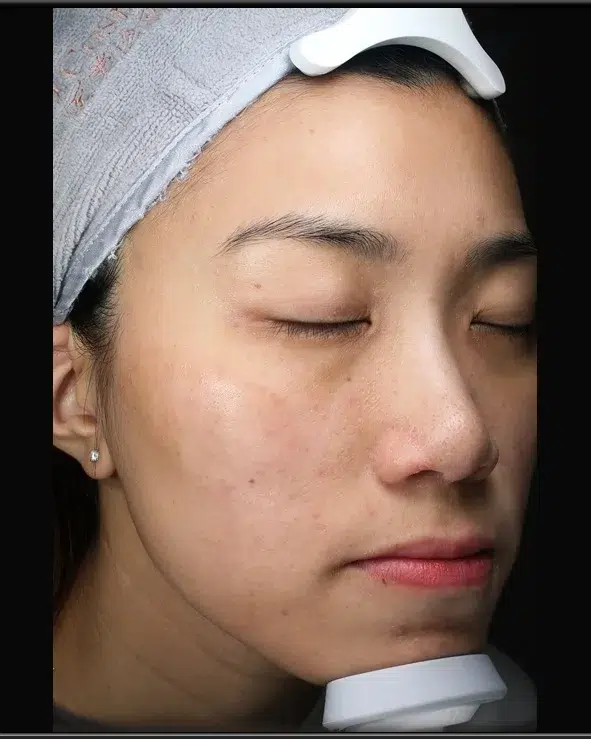
Case 21 · Documented PIH Treatment Journey
- Client profile
- Asian Female · Fitzpatrick IV · Duration: Long-term
- Primary concern
- Post-Inflammatory Hyperpigmentation (Comprehensive Improvement with Multimodal Combination Therapy)
- Treatment plan
- Dual picosecond combination treatment + PicoSure® + PicoSure Pro® + PicoWay® — 7 modalities total (1–2 sessions)
- Improvement
- Significant improvement in post-inflammatory hyperpigmentation · Natural-looking overall result
- Risk of rebound hyperpigmentation
- No PIH
- Maintenance
- Routine sun protection + monthly at-home skincare + quarterly clinical review
Case 21: Post-Inflammatory Hyperpigmentation (PIH) — Before & After · Asian Female · Fitzpatrick IV · Duration: Long-Term · Multimodal combination protocol led by our physician at Luowei Medical Aesthetics Clinic, Nanjing
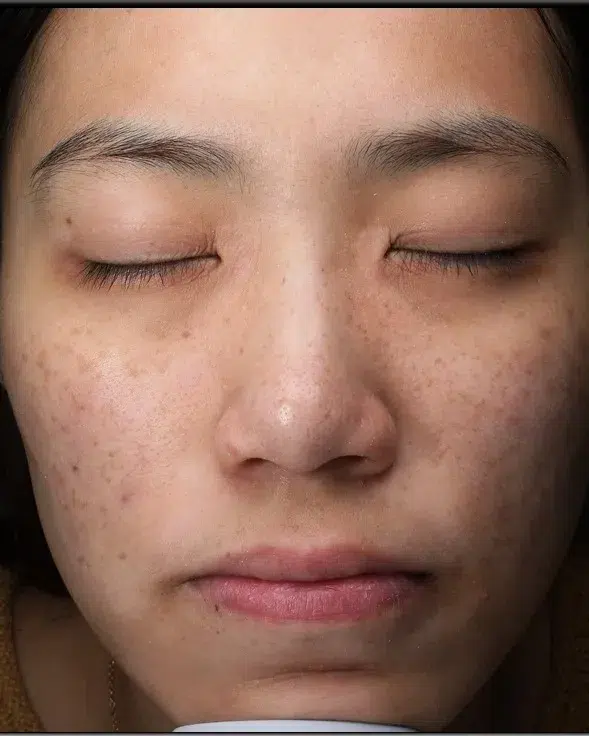
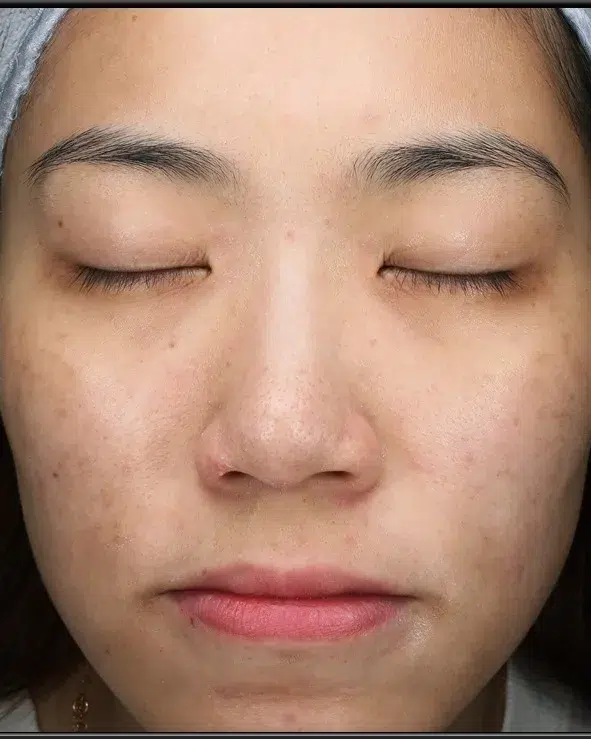
Case 22 · Post-Inflammatory Hyperpigmentation — Real Patient Record
- Client profile
- Asian Female · Fitzpatrick IV · Duration: Long-term
- Primary concern
- Post-Inflammatory Hyperpigmentation (Comprehensive Improvement with Multimodal Combination Therapy)
- Treatment plan
- Dual picosecond combination therapy + PicoSure® + PicoSure Pro® + PicoWay® and 5 other modalities (1–2 sessions)
- Improvement
- Significant improvement in post-inflammatory hyperpigmentation · Natural-looking overall result
- Risk of rebound hyperpigmentation
- No PIH
- Maintenance
- Routine sun protection + monthly at-home skincare + quarterly clinical review
Case 22: Post-Inflammatory Hyperpigmentation — Before & After · Asian Female · Fitzpatrick IV · Duration: Long-term · Multimodal combination protocol led by our physician at Luowei Medical Aesthetics Clinic, Nanjing
What is post-inflammatory hyperpigmentation (PIH)? How is it different from acne scarring and melasma?
Post-inflammatory hyperpigmentation (PIH) is a condition in which the skin, following inflammation, trauma, acne, prior mistreatment, or other irritation melanocytes respond to stress by overproducing pigment, which deposits in the epidermis and superficial dermis, leaving brown or grayish-brown marks. PIH is not the same as an “atrophic acne scar” (which involves tissue loss) or melasma (which is hormonally driven). It is the “pigment shadow” of inflammation — it can fade on its own, but the process is extremely slow, and in Asian skin it tends to be especially persistent.
Why can’t PIH simply be treated the same way as general pigmentation spots?
PIH the underlying basis is Compromised skin barrier + chronic inflammation. High-energy laser applied directly to active PIH re-stimulates melanocytes, causing pigmentation to deepen rather than fade.
Why Is PIH So Stubborn in Asian Skin?
Fitzpatrick III–V Asian skin has a higher melanocyte density and heightened stress reactivity — post-inflammatory pigment production is 5–10 times greater than in Caucasian skin, and natural clearance can take 6–24 months.
PIH What is the difference between PIH and acne scars (Acne Scar)?
PIH marks are Color concern(flat pigmented marks), while acne scars are Structural concerns(sunken or raised texture). The former is addressed with brightening treatments and barrier repair; the latter requires microneedling, fractional laser, or Subcision.
Why Must All Aggressive Actives Be Stopped First?
Clinically, 60% of PIH patients are using Overuse of active ingredients(high-dose vitamin C, high-concentration AHAs, or over-exfoliating with acids). Without first repairing the skin barrier, no treatment will deliver lasting results.
Clinical note:Many clients use a “brightening serum” consistently for six months, only to find their pigmentation darkening further. The reason is The more irritation, the more inflammation — the more pigmentation. The first step in our physician’s protocol is often not “treatment” — it is Stopping all irritants + barrier repair.
The Five Root Causes of Acne Mark Pigmentation — It’s More Than Just “Marks That Haven’t Faded”
PIH is Inflammation + barrier + pigmentation the result of a three-axis imbalance. Without identifying the underlying trigger, treatment is almost certain to result in recurrence.
1. Acne / cystic acne
Inflammatory acne penetrates into the superficial dermis; as the inflammation resolves, melanocytes respond by producing excess pigment. This is the most common cause of PIH in Asian women.
2. Inappropriate energy-based treatments (IPL or high-powered laser)
Excessive energy or parameters mismatched to skin type → thermal injury to the epidermis → melanocyte stress response → diffuse PIH. This is particularly prevalent in Asian skin types and is referred to as “iatrogenic PIH.”
3. Over-exfoliation with acids / high-concentration active ingredients
Self-applying AHAs above 30%, high-concentration retinol, or high-strength vitamin C serums — resulting in a compromised skin barrier and diffuse hyperpigmentation.
4. Physical trauma (squeezing, picking, or rubbing the skin)
Picking at acne with fingers, scrubbing vigorously with a towel, or overusing cleansing devices → repeated micro-inflammation → chronic, layered PIH.
5. Compromised skin barrier + UV synergy
When the skin barrier is compromised, the skin becomes more sensitive to UVA and visible light — even routine daily sun exposure during a commute can continuously deepen PIH pigmentation.
4 conditions commonly confused with acne-related pigmentation — key differential diagnosis points
Misidentifying PIH as melasma, acne scarring, or general hyperpigmentation is the most common frustration for Asian patients with pigmentation concerns. The table below summarizes the 4 most clinically relevant differential diagnoses from our physician’s practice.
Post-inflammatory hyperpigmentation (PIH)
Post-Inflammatory Hyperpigmentation
| Distribution | Site of original inflammation / acne / prior mistreatment |
|---|---|
| Pattern / morphology | Flat brown or grayish-brown patches |
| Symmetry | Asymmetric distribution (depends on specific triggers) |
| Triggering factors | acne, picking, inappropriate laser treatment, or chemical over-exfoliation |
| First-line treatment | Barrier repair + Fotona® ClearGlow + skin booster |
Red acne marks (PIE — post-inflammatory erythema)
Post-Inflammatory Erythema
| Distribution | Site of prior acne lesion |
|---|---|
| Pattern / morphology | Pink to dark red marks (vascular component) |
| Symmetry | Asymmetry |
| Triggering factors | Post-acne capillary dilation (telangiectasia) |
| First-line treatment | Vbeam Vascular laser + barrier repair |
Depressed acne scars (Atrophic Scar)
Atrophic Acne Scar
| Distribution | Sites of prior deep inflammatory acne |
|---|---|
| Pattern / morphology | Atrophic scarring (icepick / boxcar / rolling) |
| Symmetry | Asymmetry |
| Triggering factors | Dermal collagen disruption |
| First-line treatment | Microneedling / Fractional Laser / Subcision |
Melasma
Melasma · Melasma
| Distribution | Symmetrical across both cheeks, butterfly-shaped distribution |
|---|---|
| Pattern / morphology | Symmetrical patchy brown pigmentation |
| Symmetry | Highly symmetrical |
| Triggering factors | Hormonal factors + UV exposure + genetics |
| First-line treatment | PicoSure Pro Low-fluence treatment + long-term management |
⚠️ Warning:In clinical practice, PIH and PIE frequently coexist, yet their treatment approaches are fundamentally opposite: PIH is highly sensitive to heat and irritation, while PIE requires vascular laser intervention. Treating both without first typing them can leave PIE unresolved while worsening PIH — this is the most common “treatment failure cycle” seen in Asian patients with acne marks.
Why Does Asian Skin PIH Require a Fitzpatrick III–V Specialist Protocol?
Common blind spots in mainstream North American clinics
Most PIH treatment protocols in North America are based on data from Fitzpatrick I–II (lighter) skin types. Applying them directly to Asian Fitzpatrick III–V skin creates problems in three key areas:
- ✗ Energy overload leading to rebound hyperpigmentation— epidermal melanin concentration is 5–10× higher — the same energy level that is safe for lighter skin equates to thermal injury in Asian skin
- ✗ Neglecting skin barrier repair— Jumping straight to actives or laser treatments progressively compromises the barrier
- ✗ Treating PIH as melasma or general pigmentation— Different pathological mechanisms require different protocols — applying the wrong one is a common error
Our physician’s Specialized Adjustments for Fitzpatrick III–V Skin
| Parameters | North American standard | Asian-adjusted |
|---|---|---|
| Energy fluence | 3.0–4.0 J/cm² | 1.0–2.0 J/cm² |
| Pre-conditioning | None | 4–12 weeks of barrier repair |
| Treatment interval | 2–3 weeks | 3–4 weeks |
| Test spot | Optional | Required |
| Barrier-repair skincare | Not emphasized | Barrier-repair-focused skincare for 4 weeks |
Key differentiators:Our physician has spent 8 years focused on Asian faces in Nanjing, with over 90% of the clientele presenting Fitzpatrick III–V skin.
6 PIH Treatment Approaches — Tailored by Barrier Status and Pigmentation Depth
PIH There is no one-size-fits-all approach. Our physician selects and combines the devices and therapies below based on each patient’s barrier status, depth of pigmentation, and the presence of any concurrent PIE or atrophic scarring.
Fotona ClearGlow(FRAC3)
1064nm Long-pulse, low-energy settings — treating while Stimulates collagen production + improves vascular appearance + fades PIH, minimally disruptive to the skin barrier, making it the clinical first choice for PIH in Asian skin.
Brightening mesotherapy (glutathione + tranexamic acid)
Targeted superficial dermal microinjections inhibit tyrosinase activity and accelerate pigment turnover. When introduced during the barrier-stable phase, results are significantly superior to topical application alone.
Chemical peel (superficial lactic acid / mandelic acid)
Promotes epidermal cell turnover and gently accelerates pigment shedding. The preferred option for Asian skin types.Lactic acid / mandelic acid rather than high-concentration AHAs, to avoid triggering a new cycle of PIH.
PicoSure Pro Picosecond laser (ultra-low fluence)
755nm Ultra-short-pulse picosecond technology — applied after barrier stabilization using an ultra-low-fluence protocol to precisely target stubborn pigmentation without causing additional thermal damage.
Rejuran® skin booster (PDRN)
PDRN Repairs dermal cells and accelerates barrier restoration. Best suited for the early recovery phase following severe barrier compromise or accidental over-exfoliation with acids.
LED Healite II LED + barrier-repair skincare
Low-fluence red light anti-inflammatory therapy + Cyspera / niacinamide / barrier-repair skincare — running throughout the entire treatment course, this is the cornerstone of “treatment between sessions.”
Our physician’s 6-Step Standard Protocol for Acne PIH
Consultation + Wood’s lamp analysis + barrier assessment
30 minute free consultation — Wood’s lamp analysis to identify pigmentation depth, VISIA imaging to map pigment distribution, and TEWL testing to assess barrier function.No device is activated without first assessing barrier function.
Treatment pause + barrier recovery phase (4–12 weeks)
Discontinue all high-potency actives (AHAs, retinol, high-concentration vitamin C) and all energy-based treatments. Switch to barrier-repair skincare and a physical SPF 50+ sunscreen containing iron oxides. A healthy skin barrier is the foundation of any successful PIH treatment.
Test spot(test spot)
A test treatment is performed on a discreet area, with a 7–10 day observation period to assess the skin’s response.Essential Steps for PIH Patients with Asian Skin Types, commonly omitted by North American clinics, leading to rebound hyperpigmentation.
Active treatment phase (6–10 sessions, once every 3–4 weeks)
Fotona ClearGlow primary treatment, supported by skin booster injections / superficial chemical peels, and finished with Healite II LED therapy. After each session, apply cold compresses immediately followed by barrier-repair skincare to prevent cumulative inflammation.
Assessment phase (6–8 weeks after completing primary treatment)
Wood’s lamp Re-assessment with VISIA quantitative imaging comparison. We then determine whether to transition to a maintenance program or add further treatment.
Maintenance phase + long-term acne management
One low-fluence maintenance session every 8–12 weeks + long-term topical Cyspera / niacinamide + ongoing acne root-cause management (if not yet controlled). The key to lasting PIH clearance lies in No longer generating new inflammation.
Treatment Timeline — How Long Before You See Results?
| Type | Treatment cycle | Initial visible improvement | Significant improvement | Maintenance interval |
|---|---|---|---|---|
| Superficial PIH following acne | 4–6 sessions | After the 2nd session | After session 4 | Every 8–12 weeks |
| Acid over-exfoliation / barrier-disruption PIH | 6–8 sessions | 2nd session after skin barrier is stable | After the 5th–6th session | Every 8–10 weeks |
| IPL Post-mistreatment PIH | 8–12 sessions | After session 4 | After the 8th session | Every 6–8 weeks |
| Stubborn deep-toned PIH (deeper skin types) | 10–15 sessions | After the 5th session | After session 10 | Long-term sessions every 6–8 weeks |
Clinical note:PIH The single greatest mistake in PIH treatment is rushing. Starting laser before the barrier is stable, scheduling sessions too closely together, or using excessive energy — any one of these can deepen pigmentation by a full grade. Our clients in Nanjing who follow the structured 6–12 month protocol consistently achieve far better long-term outcomes than those who pursue aggressive, accelerated treatments.
Are you a candidate for PIH treatment? 2-minute self-assessment
✅ Ready to begin assessment
- ✓Acne / inflammation has been stable for at least 3 months without recurrence
- ✓Flat brown or grey-brown pigmentation (non-depressed) that has not resolved on its own within 3 months
- ✓Asian skin types, Fitzpatrick III–V
- ✓Previously treated elsewhere with subsequent worsening of pigmentation
- ✓Willing to discontinue all high-concentration active ingredients for 4+ weeks
- ✓Following a structured 6–12 month protocol
❌ Requires deferral or resolution of other concerns first
- ✗Active acne is still present (acne must be controlled first)
- ✗Currently pregnant or breastfeeding
- ✗Sun exposure or sunburn within the past 4 weeks, not yet recovered
- ✗Active facial eczema / dermatitis
- ✗Currently taking photosensitizing medications (including isotretinoin within the past 6 months)
- ✗Expecting complete resolution in 1–2 sessions (a common misconception)
Luowei Medical PIH Protocol vs. Standard MedSpa Approach
- ✗Proceeding with laser after a brief visual assessment, without distinguishing between PIH, PIE, or melasma
- ✗No barrier assessment — jumping straight to a standard “pigmentation package”
- ✗Energy parameters derived from Caucasian-based North American templates
- ✗No test spot performed — full-face treatment on the very first session
- ✗Treatments are often performed by aestheticians, with no physician consultation
- ✗Being told to “do another session to cover it” after experiencing rebound pigmentation
- ✗Without addressing the root cause of acne, pigmentation will return even after treatment
- ✓Mandatory pre-treatment diagnostics: Wood’s lamp + VISIA + TEWL assessment
- ✓No energy-based treatment until barrier stability is confirmed
- ✓Fitzpatrick III–V Specialist-calibrated parameters
- ✓Mandatory test spot + 4-week barrier pre-conditioning
- ✓Personally consulted and performed by our physician
- ✓Post-inflammatory rebound risk monitoring + proactive treatment-pause and recovery protocol
- ✓Addressing the acne root cause alongside PIH treatment to prevent recurrence
Why trust Luowei Medical Aesthetics Clinic for PIH treatment?
Experience
Expertise Areas of expertise
Authoritativeness Authority / expertise
Trustworthiness Trustworthy
All cases on this page are published with a signed Media Release Form · Clinical records on file
About the Cost of Acne PIH Treatment
Pricing for PIH treatment varies widely between clinics — but the real cost driver is not the device itself. It comes down to who performs the assessment, who determines the treatment pace, and how deeply clinical expertise needs to be involved. The complexity of PIH is frequently underestimated: it requires evaluating skin barrier status, determining the depth of pigmentation, identifying concurrent post-inflammatory erythema (PIE) or atrophic scarring, addressing the underlying acne root cause if present, and reviewing any history of prior mistreatment. Cases of this nature involve our physician directly, and the pricing reflects that level of medical resource investment. For clients whose PIH has stabilized and who simply need ongoing maintenance, our trained clinical team can deliver care under our physician’s established protocolperformed safely and accessibly. The price difference in laser treatments fundamentally reflects the clinical experience gap between physician-performed and technician-performed procedures; all injectable treatments are performed exclusively by our physician. The right treatment plan is determined by your skin condition — not by price — and will be discussed in detail during your consultation, alongside a barrier assessment and Wood’s lamp skin typing.
- Payment is made at the clinic, after the consultation and before treatment begins
- Nothing is paid in advance, and no deposit is required to hold an appointment
- Cosmetic treatment is a self-pay item and is not covered by public medical insurance in China
- All new patients receive a complimentary 30-minute Free Consultation & assessment
Risks & Contraindications — What You Need to Know
What are the main risks?
1. Rebound hyperpigmentation and worsening of pigmentation(moderate risk in Asian skin) — significantly reduced through barrier preconditioning, test spot, and low-fluence protocols; 2. Temporary redness / dry flaking (common, resolves within 1–5 days); 3. Stinging sensation during treatment (well-tolerated; cold compresses or topical anesthetic available); 4. Rare blistering / crusting (uncommon when protocols are appropriate); 5. PIH recurrence (if the underlying acne or inflammatory trigger has not been controlled).
Who is absolutely not a candidate?
Pregnancy, breastfeeding, oral isotretinoin within the past 6 months, unresolved sunburn within the past 4 weeks, active facial inflammation or acute acne, severe keloid tendency not yet assessed, photosensitive conditions, and unrealistic expectations (believing 1–2 sessions can fully resolve PIH) — in any of these situations, our physician will recommend postponing treatment or addressing the underlying issue first.
How can the risk of rebound pigmentation be minimized during treatment?
Five essential safety principles: (1) always perform a test spot first; (2) never proceed with laser treatment until the skin barrier is stable; (3) start at the lowest effective energy setting and titrate upward gradually; (4) apply a physical SPF 50+ sunscreen (containing iron oxide) for at least 4 weeks before and after each session; (5) apply cold compresses immediately post-treatment and follow with barrier-repair skincare — if redness persists beyond 7 days, return for a follow-up promptly.
What does the informed consent form include?
Every client signs an informed consent form before their first treatment. It covers: the treatment mechanism, possible adverse reactions and their likelihood, alternative options, criteria for pausing treatment, follow-up scheduling, and an optional Media Release. Our physician personally walks through every item — it is never delegated to administrative staff.
Where the medical claims on this page come from
Everything above about Post-Inflammatory Hyperpigmentation (PIH) rests on published evidence rather than on our own word. The sources below are the ones behind those statements: peer-reviewed papers indexed in PubMed, and guidance written for patients by dermatology academies and national health services. Read them before you decide — and bring any of them to your consultation.
- Peer-reviewedGuidelines of care for the management of acne vulgaris
- Peer-reviewedPostinflammatory hyperpigmentation: A comprehensive overview: Epidemiology, pathogenesis, clinical presentation, and noninvasive assessment technique
- Peer-reviewedMelasma Treatment: An Evidence-Based Review
- Peer-reviewedChemical peels for darker skin types
- Patient guidanceAcne: Tips for managing
- Patient guidanceMelasma: Treatment
What these references can and cannot tell you. They describe what is known about the treatment itself — how well it tends to work, how long results last, and what can go wrong. They are not an assessment of this clinic, and no published study can tell you whether it suits your skin type, anatomy, or medical history. That judgement comes from the physician who examines you in person, and it may well be “not this one”.